English translation updated . This article reflects the source material at its original publication date. Read the Chinese source.
Complicated urinary tract infection describes recurrent or persistent urinary infection in the presence of structural or functional abnormalities, such as obstruction or stones, or accompanying illnesses, such as diabetes or cancer. Most are bacterial. They can substantially affect quality of life and threaten kidney or bladder function.
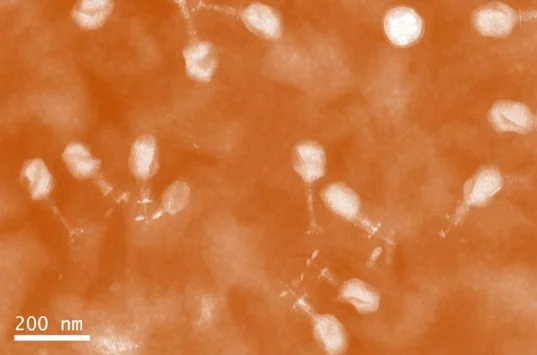
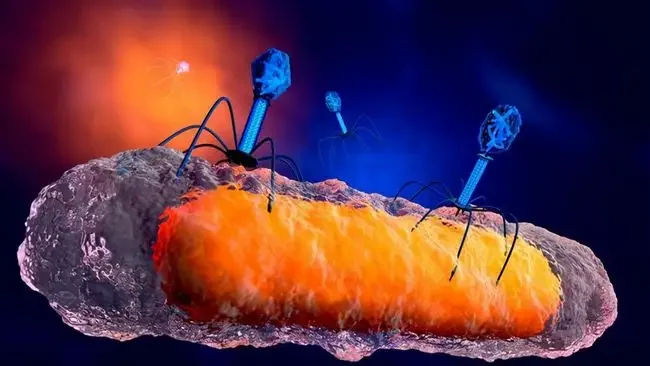
Treatment therefore involves identifying and addressing the underlying anatomical or functional problem, as well as identifying the pathogen and using an effective antimicrobial treatment. Increasing antibiotic resistance has renewed interest in phages as a possible alternative or complement to antibiotics. The following clinical case illustrates our experience in this setting.
A clinical case
Mr Han had been diagnosed with lymphoma several years earlier and had received multiple courses of chemotherapy. His general health deteriorated, and damage to the central nervous system caused difficulty passing urine, requiring an indwelling catheter. For nearly six months, he had experienced pain in the bladder region and fever reaching 39°C. Purulent, bloody urine drained through the catheter. Treatment at several hospitals had produced little improvement.
His history suggested a complicated urinary tract infection. We obtained a urine bacterial culture, tested the isolates for antibiotic susceptibility and performed urinary tract imaging. The culture identified carbapenem-resistant Pseudomonas aeruginosa. CT showed multiple bladder stones and widespread inflammatory changes in the bladder wall, establishing both the infection and an underlying cause.
Antibiotic treatment before admission had not resolved his symptoms. The patient expressed a strong interest in phage therapy. Following informed consent, we screened lytic phages against his urinary P. aeruginosa isolate and prepared a personalized cocktail. This was administered by bladder instillation alongside intravenous antibiotics.
After two days of phage treatment, the patient underwent cystoscopic holmium laser fragmentation and removal of the bladder stones. Bladder instillation of phages continued for three days after surgery, completing a five-day course. His urinary symptoms improved substantially, and repeated urine cultures no longer detected the pathogen. The source reports resolution of the infection following the combined treatment.
Delivering phages to a urinary infection
The urinary tract communicates with the outside environment. This can provide a route for pathogens to enter, but also allows local delivery of phage preparations. The original article discusses bladder instillation for lower urinary tract infection. For upper urinary tract infection, it describes specialist procedures such as retrograde catheterization to the renal pelvis for sampling and local delivery, or antegrade delivery through a nephrostomy in the presence of severe obstruction.
These are clinical procedures described for the relevant treatment setting. Their purpose is to bring an appropriate preparation into contact with the target bacteria. Phages do not move independently through the urinary tract; delivery must reach the infection site. The article emphasizes adequate distribution and exposure, particularly where an infection involves a localized focus or biofilm. Following control of the infection, damaged urinary epithelium may recover and restore its barrier function.
Why addressing the underlying problem matters
Controlling bacteria alone does not correct the structural or functional abnormalities that sustain a complicated infection. Urinary stones can obstruct flow and damage the urinary tract. Stones and long-term catheters can also provide surfaces for bacterial attachment and biofilm formation, which can reduce the effectiveness of antibiotics.
In the case described, removal of the bladder stones was an essential part of treatment. Recovery of urinary function and, where feasible, removal of an indwelling catheter also matter when addressing a persistent infection. Local delivery to the bladder may not adequately reach an upper urinary tract infection, which is why the article discusses catheter-based or nephrostomy-assisted delivery in appropriate specialist settings.
Safety and unresolved questions
Broad-spectrum antibiotics can act against several bacterial species, including organisms that form part of the normal microbiota. Disruption of those communities may contribute to effects such as diarrhea, nausea or gastrointestinal discomfort. Phages have a more specific relationship with their bacterial hosts; many act against only certain strains within a species. The lytic phages selected for treatment are therefore screened against the patient's target isolate.
Phages infect bacteria rather than human cells. The original article presents this specificity as a rationale for investigating their safety and their potential to spare non-target bacteria. It does not, by itself, establish the safety of every preparation or route of administration.
There are important uncertainties. Bacteria may become resistant to phages. Optimal titers, delivery methods and treatment durations have not been standardized across indications. The infection site, the patient's immune status and the pathogen can all influence outcomes.
A sufficiently diverse phage bank is needed to support screening against clinical isolates. Further work is also required on phage pharmacodynamics and pharmacokinetics, and on interactions among phages, bacteria and the human immune system. These questions make phage therapy an area for continued investigation in the response to drug-resistant bacterial infections.